
2.20
Previous Caesarean Delivery
Obstetrics & Gynaecology Protocols, Version 3.0, 2017. Chapter 2, Labour Ward.
Clinical description
Pregnancies with previous cesarean delivery are at increased risk of uterine rupture, hemorrhage, abnormal placentation, and perinatal morbidity and mortality.
Adverse outcomes coupled with anticipated litigation have led to routine preference of elective repeat cesarean deliveries.
However, planned VBACs in women with one previous cesarean delivery can be successful. Success rates vary between 70- 75%.
Several large studies of women with one prior low transverse uterine incision reported a uterine rupture rate of approximately 0.5–0.9% with VBAC.
Signs and symptoms
Documentation of the previous cesarean delivery, especially indication, outcome, and complications and any subsequent vaginal delivery should be reviewed prior to deciding on vaginal birth after cesarean or elective repeat cesarean delivery
Treatment
Mode of delivery
- Counsel patient on mode of delivery during antenatal visits. Decision to be made jointly by patient and obstetrician.
- Document decision clearly in file
- If repeat caesarean delivery is chosen, then discuss and document the plan for the situation when labour starts prior
to the scheduled date of surgery
- Consultant review (with details of previous surgery) is needed if:
- VBAC is desired with previous caesarean delivery that was not uncomplicated with low transverse uterine
incision
- Previous diagnosis of CPD led to caesarean or instrumental delivery
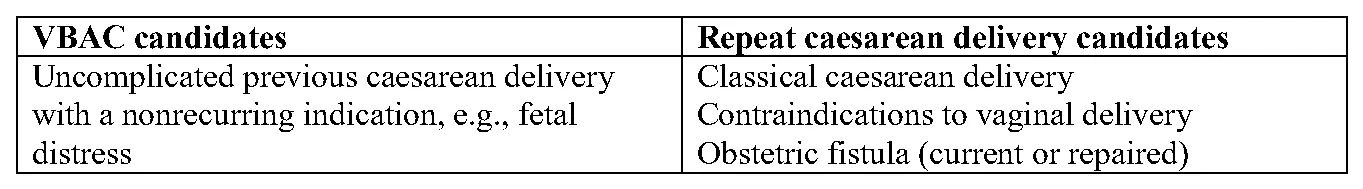
VBAC candidates Repeat caesarean delivery candidates Uncomplicated previous caesarean delivery Classical caesarean delivery with a nonrecurring indication, e.g., fetal Contraindications to vaginal delivery distress Obstetric fistula (current or repaired)
- Send blood for FBC and X-match so that blood transfusion is readily available if needed.
- Place IV line and foley catheter
- Serial cervical assessments by the same person is preferred
- Monitoring with continuous CTG during labor
- Delivery by obstetrician or experienced midwife
- Inform anaesthetist and neonatologist of possible emergencies
- Induction or augmentation of labor is not recommended given the current setting.
- Patients who opt for a trial of labor should come in in spontaneous labor.
- At most an amniotomy can be performed if possible.
Elective repeat caesarean delivery
- Delivery by senior house officer if scheduled; if emergent, then delivery by registrar or above
- Send blood for X-match so that BT is readily available if needed
- If previous classical cesarean section, schedule for elective repeat at 37 weeks gestation
Tables and figures
Check doses against the printed guideline and your clinical judgement before treating a patient. Spotted an error? Report it from the contact links below.
Need this without data?
The app holds every guideline on your device, with calculators, bookmarks and notes.