
4.1
AVD — Key Facts & Diagnosis
Guidelines for Management of Sexually Transmitted Infections, 5th Edition, 2025. Chapter 4, Abnormal Vaginal Discharge (AVD).
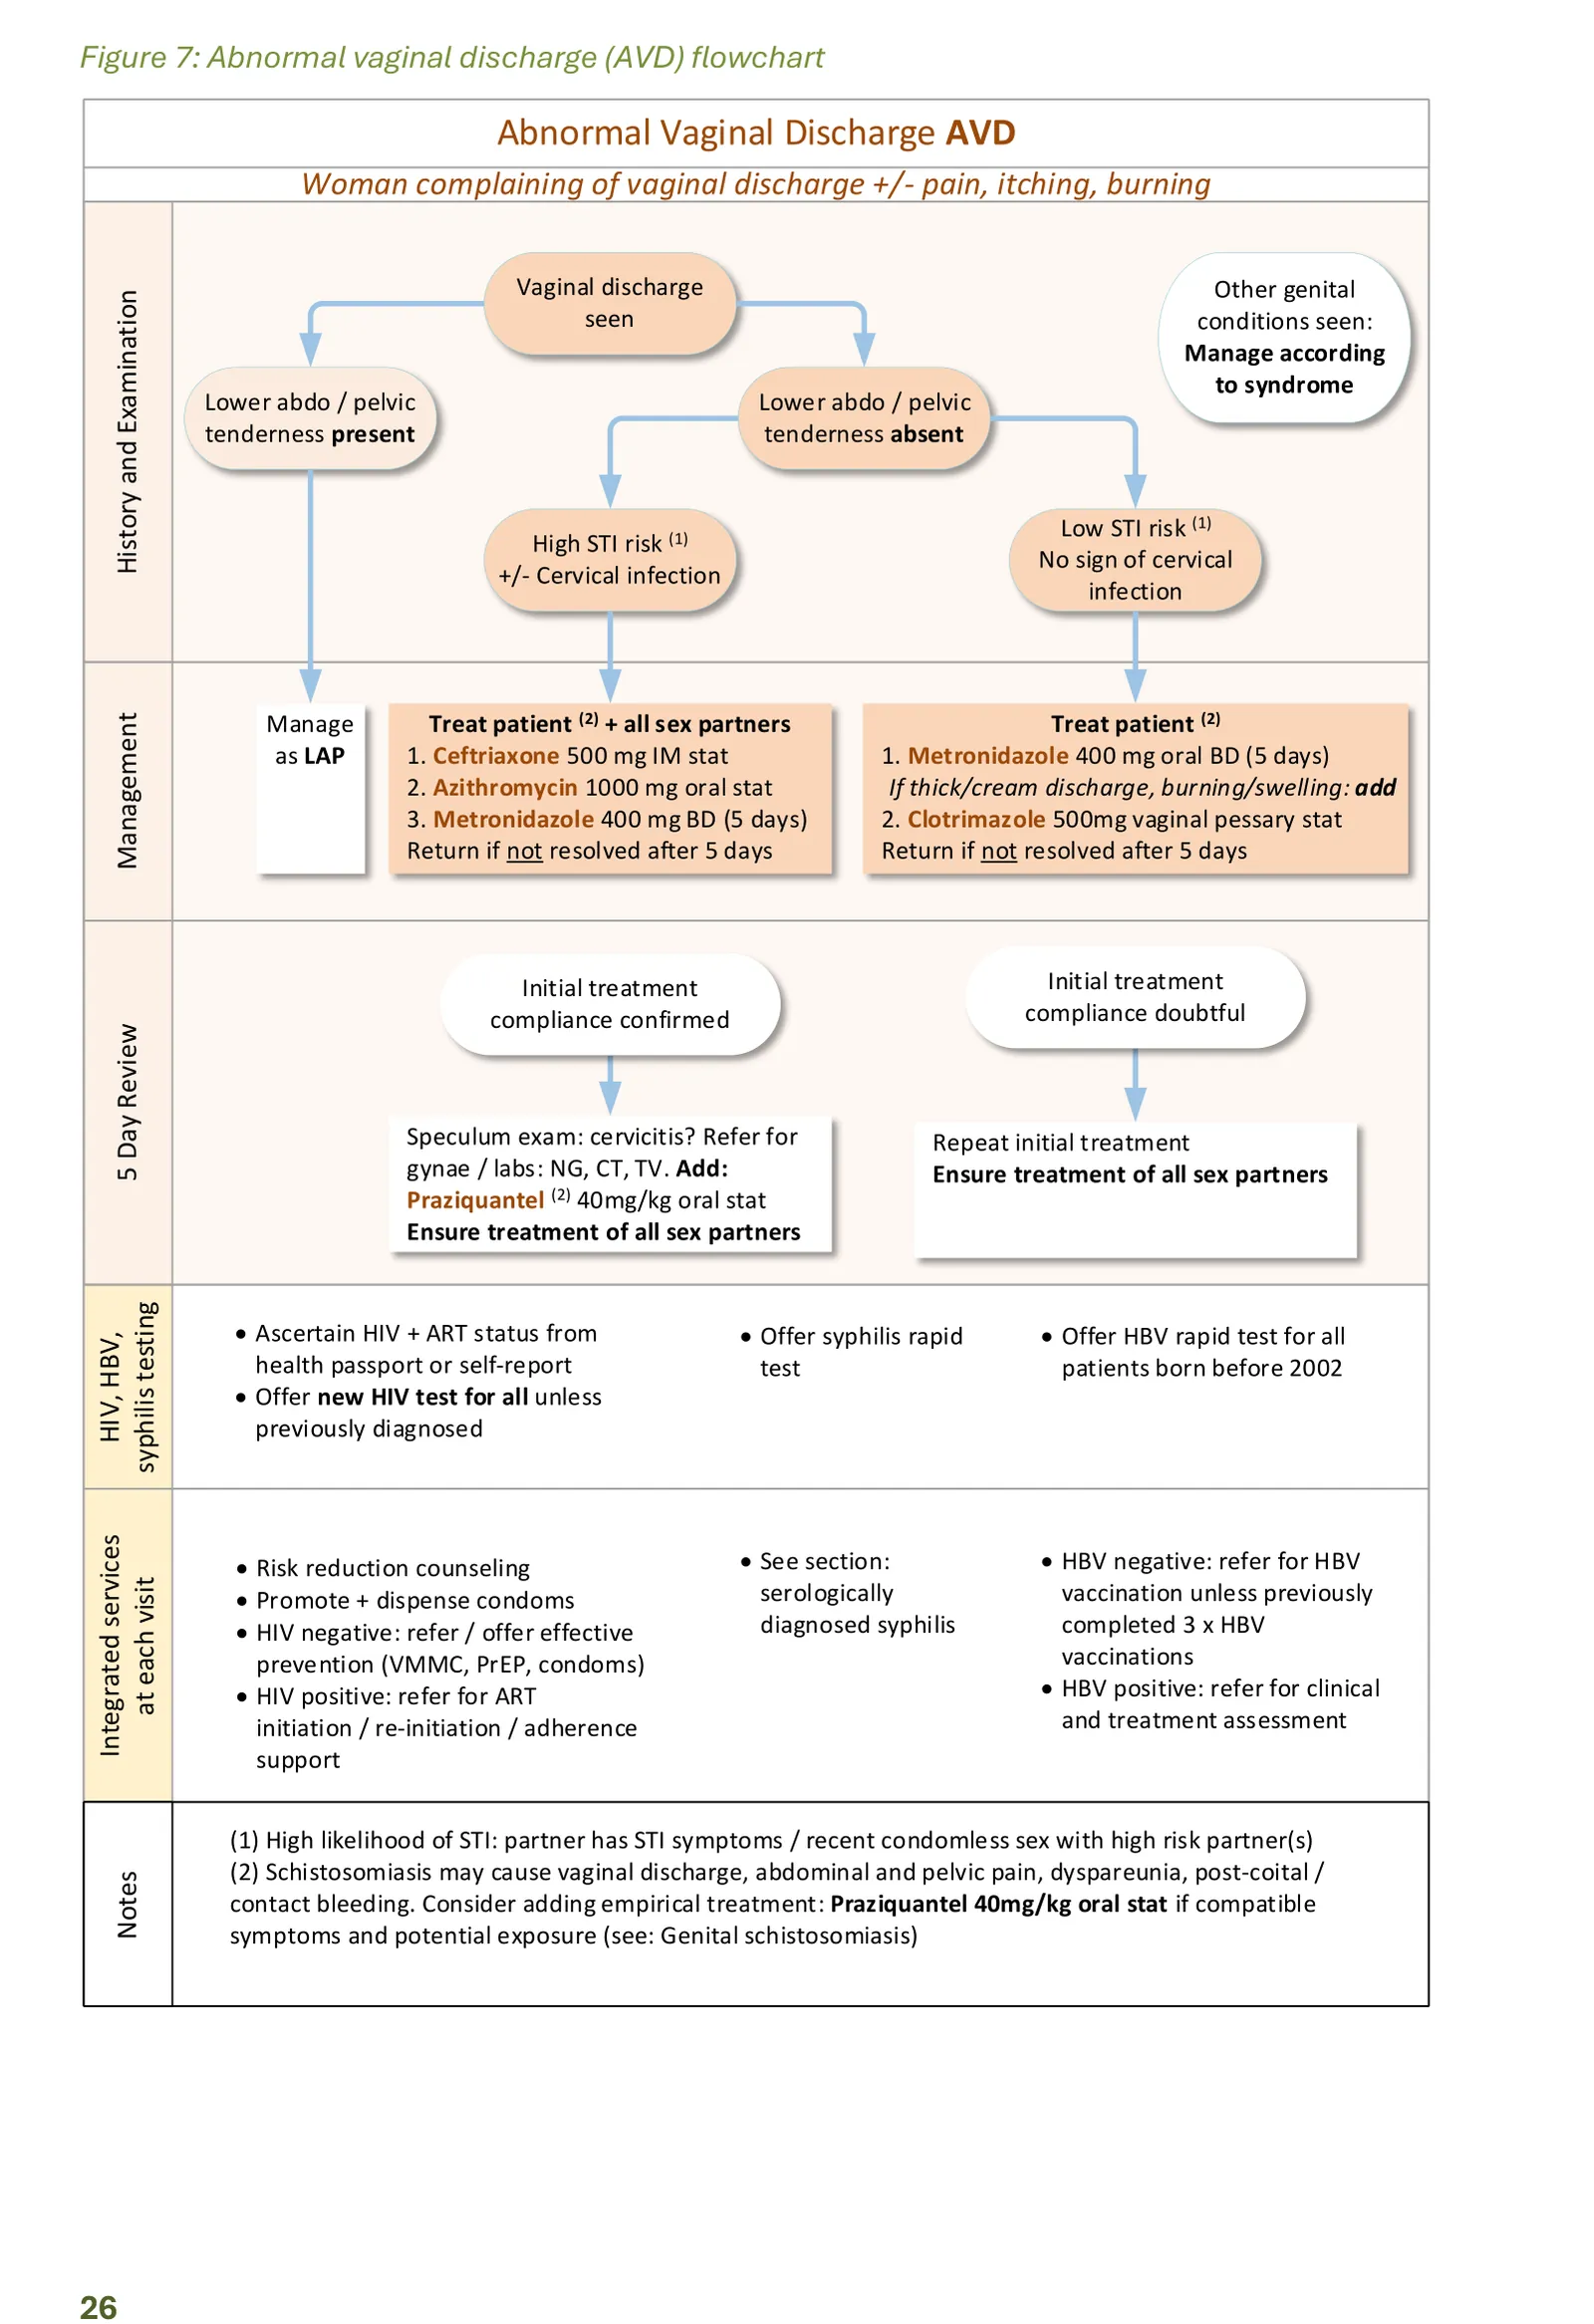
Clinical description
- Main symptoms: vaginal discharge with abnormal quantity/consistency/colour/odour. ± itching, soreness, swelling, dyspareunia, dysuria. ± lower abdominal/pelvic pain (if present, manage as LAP).
- Sexually transmitted causes: Trichomonas vaginalis, Neisseria gonorrhoea, Chlamydia trachomatis — can spread to upper genital tract causing PID.
- Non-sexually transmitted causes: Candida albicans, bacterial vaginosis (foul odour), genital schistosomiasis.
- Use sexual risk assessment to distinguish STI from non-STI causes. High STI risk: partner has STI symptoms and/or recent condomless sex with high-risk partner(s), or any sign of cervical infection.
- Routine syphilis screening is useful in women with AVD to diagnose asymptomatic syphilis.
Treatment
Always perform pelvic/abdominal palpation and speculum exam for women with AVD to rule out cervical cancer and PID. Follow LAP management if any tenderness is present.
High STI risk / cervicitis — standard treatment
- Ceftriaxone 500 mg IM stat.
- Azithromycin 1000 mg oral stat.
- Metronidazole 400 mg oral BD for 5 days.
Low STI risk / no cervicitis — standard treatment
- Metronidazole 400 mg oral BD for 5 days.
- If thick/cream discharge, burning/swelling: add clotrimazole 500 mg vaginal pessary stat.
Return if not resolved after 5 days. Add praziquantel 40 mg/kg if compatible with genital schistosomiasis.
Partner treatment
Partner treatment (asymptomatic)
- Low STI risk: no routine treatment for partners.
- High STI risk / cervicitis: ceftriaxone 500 mg IM stat + azithromycin 1000 mg oral stat + metronidazole 2000 mg oral stat.
At every visit
HIV & ART status
- Ascertain HIV + ART status from health passport or self-report.
- Offer new HIV test for all unless previously diagnosed. Do not use coercion.
- New positive: active referral for ART initiation.
- New negative: refer/offer PrEP, VMMC, consistent condom use.
- Known positive: reinforce ART adherence or refer for re-initiation.
Hepatitis B
- Offer HBV rapid test for all patients born before 2002.
- HBsAg negative: refer for HBV vaccination unless previously completed 3 doses.
- HBsAg positive: refer for clinical and treatment assessment.
Syphilis screening
- Offer syphilis rapid test for concurrent asymptomatic syphilis (except in GUD/ARI where it does not influence treatment decisions).
Risk reduction & condoms
- Risk reduction counselling. Promote and dispense condoms.
- Promote VMMC for all non-circumcised men. Schedule appointment in 2 weeks.
Tables and figures
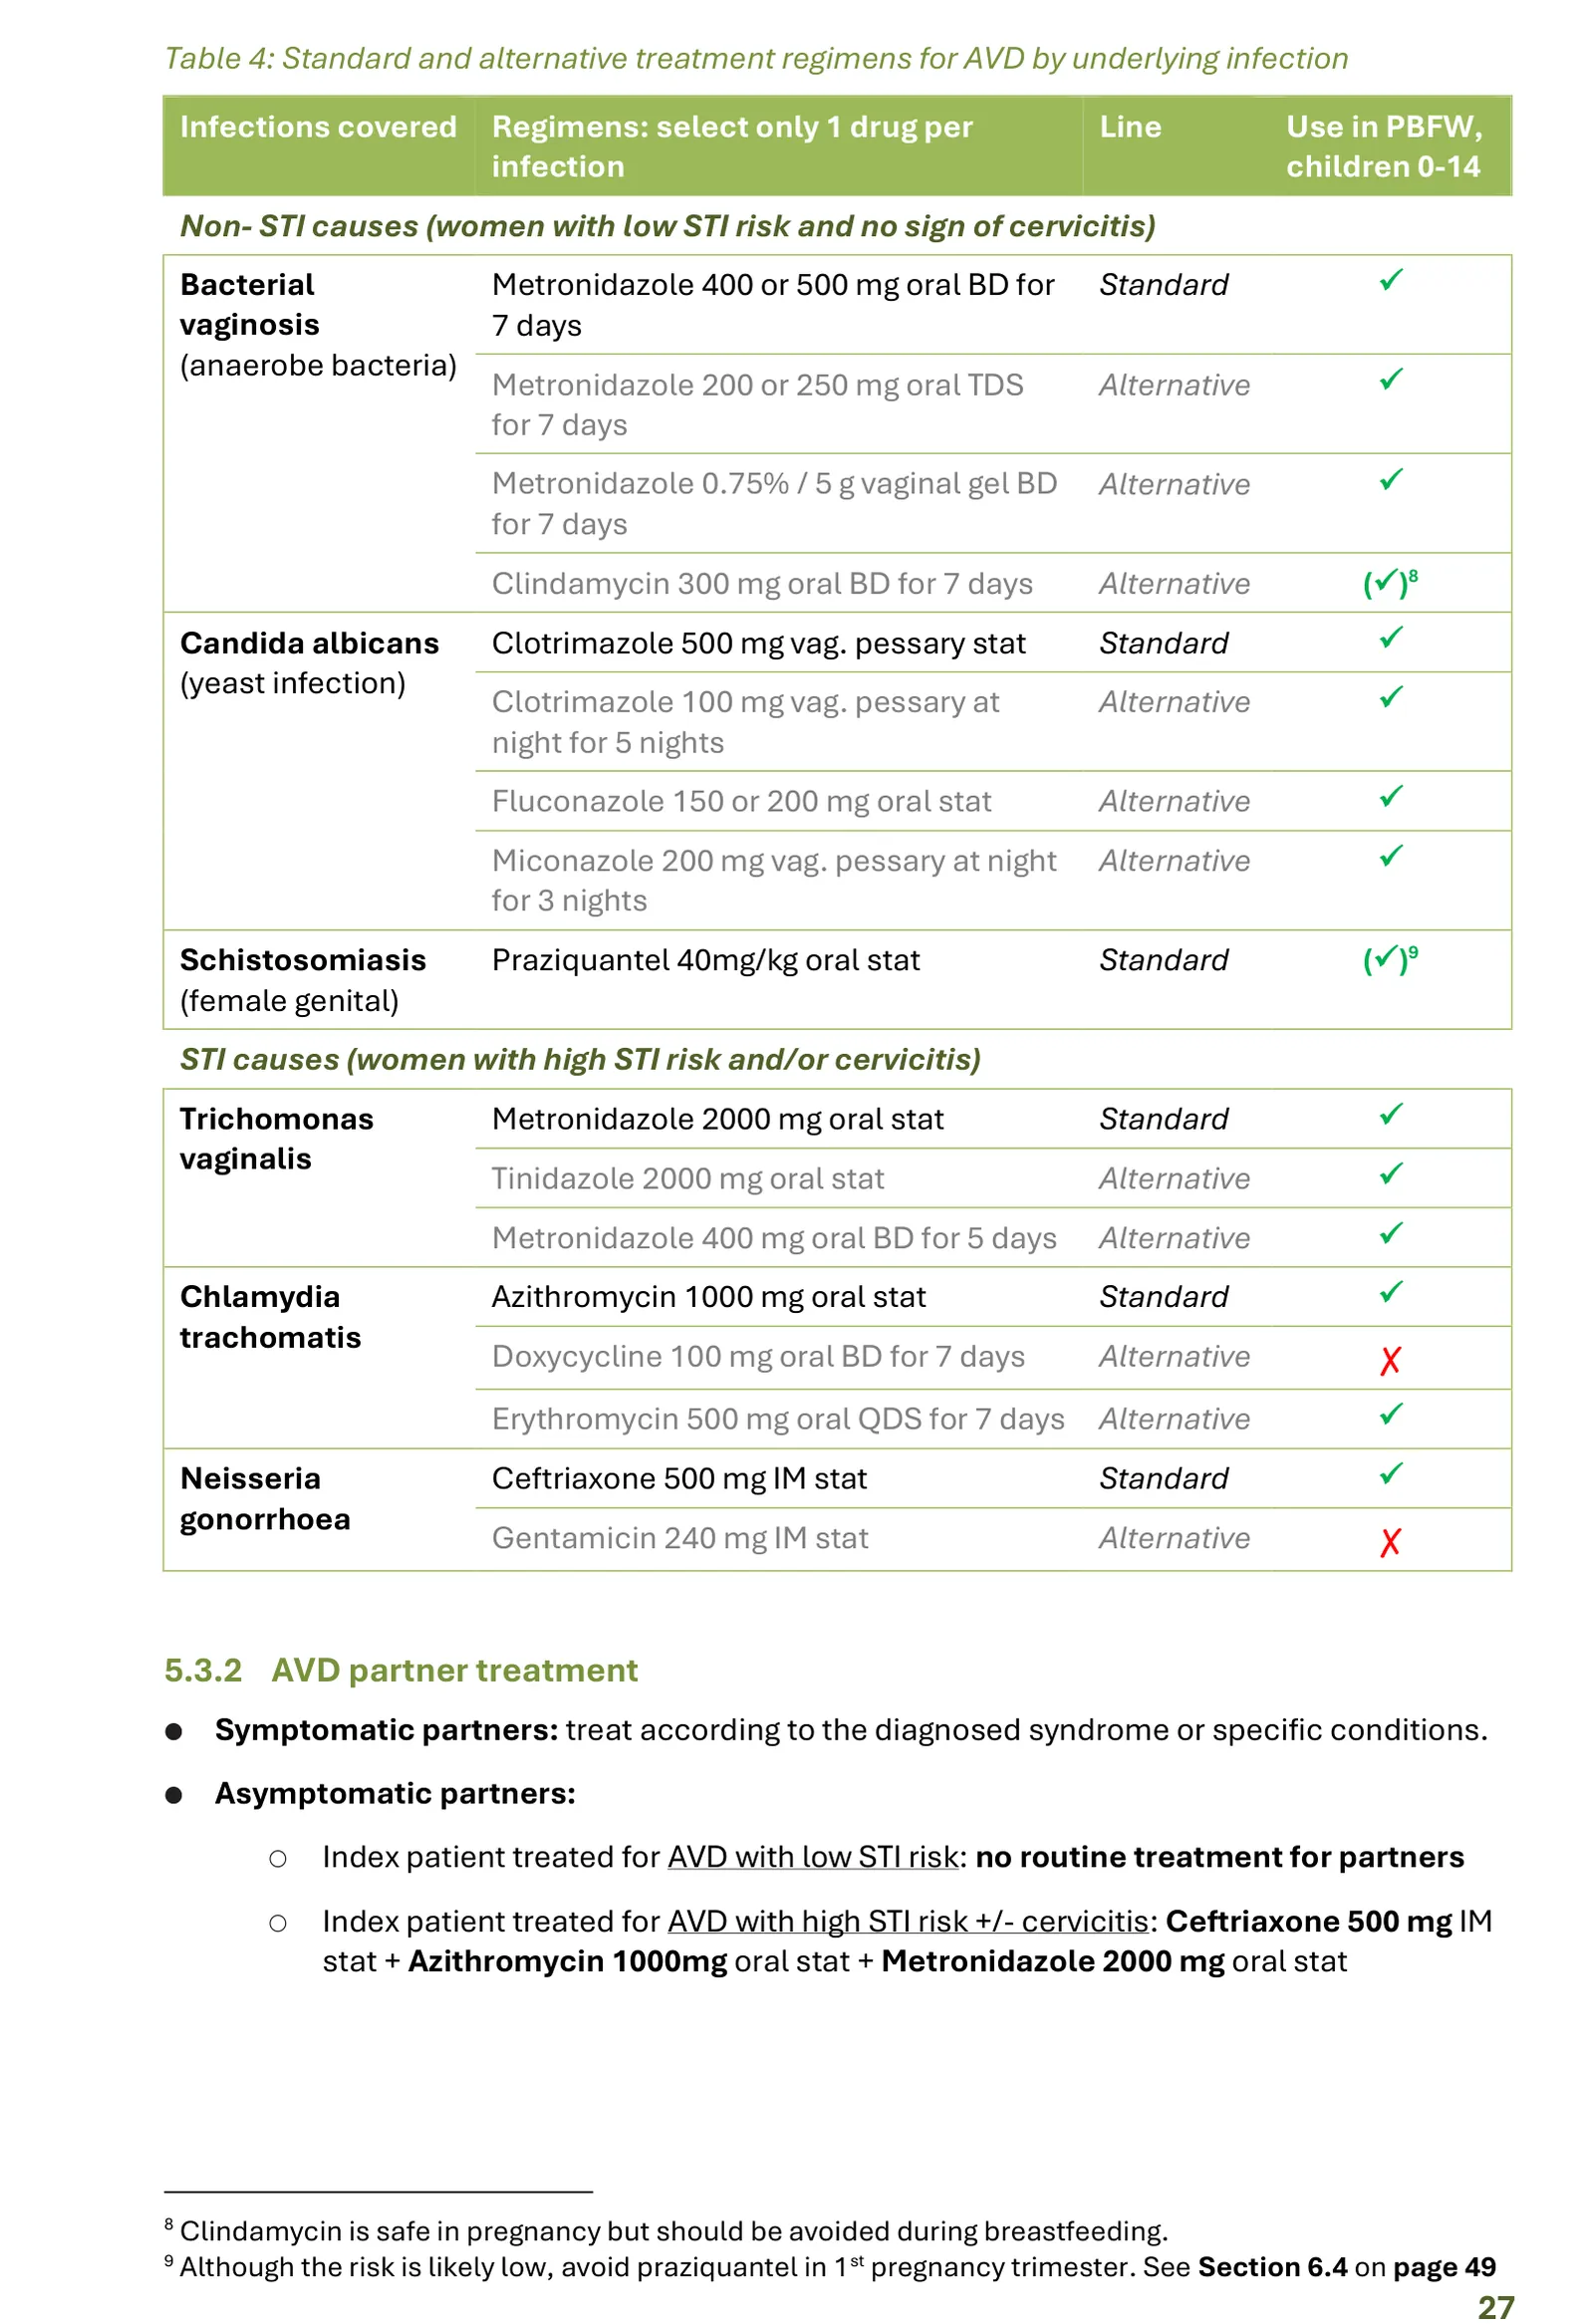
Check doses against the printed guideline and your clinical judgement before treating a patient. Spotted an error? Report it from the contact links below.
Need this without data?
The app holds every guideline on your device, with calculators, bookmarks and notes.